
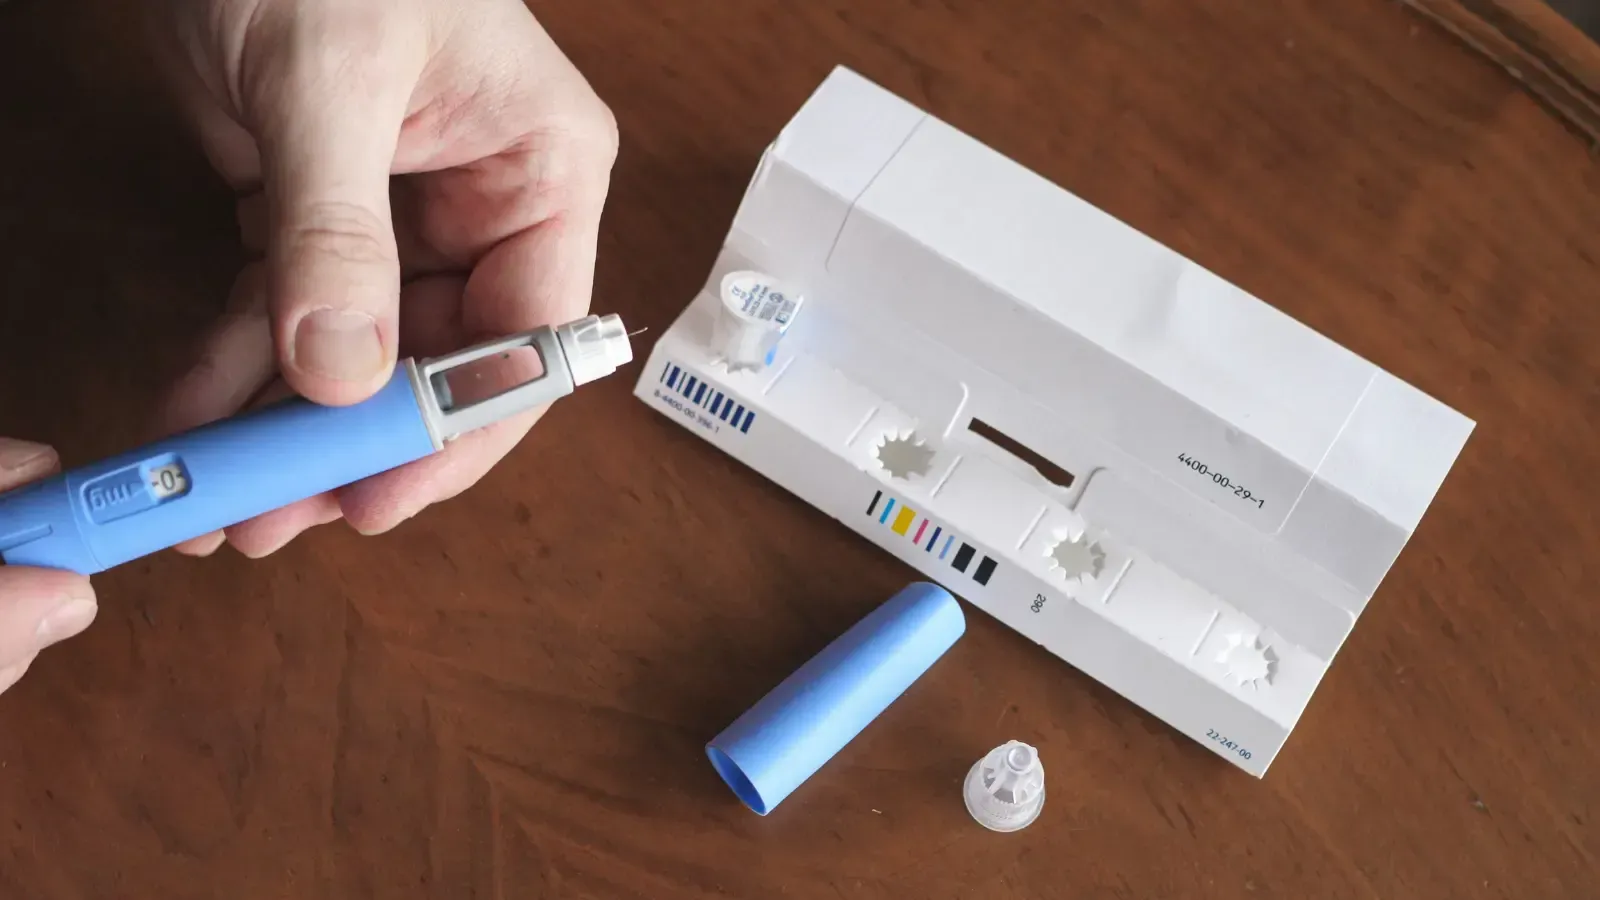
Few pharmaceutical developments in modern history have ignited as fierce a cultural and medical debate as the rise of GLP-1 receptor agonists. Marketed under brand names that have rapidly entered the common vernacular, semaglutide has transitioned from a specialized endocrine therapy into a global phenomenon.
Public discourse surrounding the drug routinely polarizes into two unhelpful narratives: either it is championed as an effortless biological miracle that renders dietary discipline obsolete, or it is demonized as an artificial, hazardous vanity shortcut destined for catastrophic collapse.
For clinical practitioners and women seeking objective health literacy, both perspectives miss the mark. Semaglutide is neither magic nor poison; it is a potent, targeted hormonal therapy that profoundly alters metabolic and neurochemical pathways.
Understanding its true physiological mechanisms, its distinct pharmacological formulations, and its profound impact on musculoskeletal composition is essential for evaluating its role in modern medicine.
The Incretin System: What Semaglutide Actually Is
To understand semaglutide, one must understand the incretin hormone system. When food enters the gastrointestinal tract, specialized enteroendocrine L-cells in the distal ileum and colon secrete glucagon-like peptide-1 (GLP-1).
Endogenous GLP-1 performs several vital metabolic tasks: it stimulates glucose-dependent insulin secretion from pancreatic beta cells, suppresses inappropriate postprandial glucagon secretion, and delays gastric emptying. However, natural human GLP-1 has a biological half-life of less than two minutes, rapidly degraded by the circulating enzyme dipeptidyl peptidase-4 (DPP-4).
Semaglutide is a synthetic GLP-1 receptor agonist engineered with structural modifications—specifically an amino acid substitution at position 8 and an attached fatty diacid chain. These modifications shield the molecule from enzymatic breakdown and allow it to bind reversibly to albumin, extending its active half-life to approximately one week. This molecular engineering enables steady, once-weekly subcutaneous dosing.
Clarifying the Brand Divide: Ozempic Versus Wegovy

A major source of widespread confusion is the imprecise use of brand names. While both medications utilize semaglutide as their active pharmaceutical ingredient, they carry distinct clinical indications, dosing schedules, and regulatory approvals.
Developed by Danish pharmaceutical manufacturer Novo Nordisk, Ozempic received initial approval from the U.S. Food and Drug Administration in December 2017 exclusively for the management of glycemic control in adults with type 2 diabetes mellitus, capped at maximum maintenance doses of 1.0 mg or 2.0 mg weekly.
Recognizing the substantial, dose-dependent reduction in body mass observed during diabetic clinical trials, researchers initiated dedicated trials investigating higher dosing specifically for chronic adiposity.
In June 2021, the FDA formally approved Wegovy—a higher-dose formulation reaching 2.4 mg weekly—specifically for chronic weight management in adults with a body mass index (BMI) of 30 or greater, or a BMI of 27 or greater in the presence of at least one weight-related metabolic comorbidity, such as dyslipidemia, hypertension, obstructive sleep apnea, or cardiovascular disease. While Ozempic has been widely prescribed off-label for weight management due to systemic supply shortages, Wegovy remains the formally designated therapeutic version for this indication.
The Neurobiology of Satiety and the Silencing of "Food Noise"
The metabolic impact of semaglutide extends far beyond simple gastrointestinal mechanics. Its most transformative action takes place within the central nervous system.
Semaglutide traverses the semi-permeable median eminence to access GLP-1 receptors in the arcuate nucleus of the hypothalamus, the metabolic control tower of the brain. Here, it stimulates pro-opiomelanocortin (POMC) and cocaine- and amphetamine-regulated transcript (CART) neurons, which generate powerful satiety signals. Concurrently, it inhibits adjacent neuropeptide Y (NPY) and agouti-related peptide (AgRP) neurons, which are responsible for driving acute hunger and foraging behavior.
Simultaneously, semaglutide binds to receptors in the mesolimbic dopamine pathway—the brain’s central reward circuitry located in the ventral tegmental area and nucleus accumbens. By modulating dopaminergic signaling, semaglutide blunts the neurological reward anticipation typically triggered by hyper-palatable, calorie-dense foods rich in refined sugars and fats.
Patients frequently describe this phenomenon as the silencing of "food noise"—the relentless, subconscious preoccupation with cravings and food procurement that characterizes many metabolic disorders.
In the gastrointestinal tract, semaglutide activates the physiological "ileal brake," substantially delaying gastric motility and gastric emptying. Food remains within the stomach for an extended duration, mechanoreceptors signal continuous fullness to the vagus nerve, and postprandial caloric intake drops organically.
The Clinical Data: The STEP Trials
The efficacy profile of semaglutide is backed by extensive, rigorous clinical data. In the landmark STEP-1 trial (Semaglutide Treatment Effect in People with Obesity), published in the New England Journal of Medicine, researchers tracked 1,961 adults across a 68-week randomized, double-blind protocol.
Participants receiving 2.4 mg of semaglutide alongside standardized lifestyle interventions achieved an average total body weight loss of 14.9%, compared to just 2.4% in the placebo group receiving lifestyle intervention alone. More than one-third of participants in the treatment arm lost greater than 20% of their total baseline body mass.
Beyond cosmetic reduction, participants demonstrated substantial, statistically significant improvements in cardiometabolic risk markers, including reductions in systolic and diastolic blood pressure, glycated hemoglobin (HbA1c), fasting insulin, and high-sensitivity C-reactive protein (hs-CRP), alongside significant improvements in circulating lipid fractions and non-alcoholic fatty liver parameters.
The Sarcopenia Dilemma: Protecting Lean Muscle Architecture
Despite its dramatic efficacy in total mass reduction, semaglutide presents a critical physiological challenge that modern sports medicine and clinical nutrition monitor with acute concern: the accelerated loss of lean skeletal muscle mass.
Rapid, severe caloric restriction inevitably prompts the body to catabolize both adipose tissue and lean lean mass for endogenous energy. Dual-energy X-ray absorptiometry (DEXA) sub-studies from major incretin trials demonstrate that between 25% and 40% of the total mass lost on GLP-1 therapies can come from lean soft tissue and skeletal muscle.
This degree of lean mass wasting carries profound metabolic implications, particularly for women. Skeletal muscle is the body’s primary metabolic engine, serving as the largest sink for postprandial glucose disposal and the primary driver of basal metabolic rate.

Losing significant muscle mass during treatment lowers resting metabolic expenditure, compromises physical stability, accelerates the decline in bone mineral density, and sets the stage for sarcopenic obesity—a clinical condition in which an individual weighs less but has an unhealthily high ratio of visceral fat to functional muscle.
To counteract this vulnerability, clinical nutrition mandates aggressive countermeasures while on incretin therapies: daily dietary protein intake must be elevated to 1.5 to 2.0 grams per kilogram of ideal body weight, accompanied by structured, progressive resistance training to provide the mechanical tension required to signal muscle preservation.
The Discontinuation Paradox: Understanding Biological Adaptation
Perhaps the most crucial, sober reality regarding semaglutide therapy is that it operates as a biological treatment for a chronic condition, rather than a permanent cure.
The STEP-1 Extension trial followed participants for one full year after the discontinuation of semaglutide and lifestyle interventions. The clinical findings were definitive: within 52 weeks of ceasing the medication, participants regained approximately two-thirds of their lost body weight, alongside an immediate rebound in blood pressure, fasting glucose, and lipid markers back toward baseline levels.
This rebound is not a failure of individual discipline or moral resolve; it is the predictable execution of human evolutionary biology.
When body mass declines rapidly, the body initiates adaptive thermogenesis: circulating leptin plummets, resting metabolic rate downregulates to conserve energy, and circulating concentrations of orexigenic hormones like ghrelin surge to drive appetite. While semaglutide is actively administered, its pharmacological potency masks these adaptive starvation signals. The moment the receptor agonist is cleared from the bloodstream, the underlying neuroendocrine drive to restore lost energy reserves reasserts itself with unmitigated force.
Safety Profiles, Adverse Reactions, and Contraindications
While generally manageable when titrated gradually, semaglutide carries documented physiological risks that necessitate careful clinical oversight.
The most prevalent adverse reactions are gastrointestinal in nature. Nausea, episodic vomiting, persistent diarrhea, and severe constipation occur in a significant percentage of patients, particularly during weekly dose-escalation phases. In rarer instances, the profound inhibition of gastric motility can precipitate clinical gastroparesis (stomach paralysis) or intestinal obstruction.
More serious, documented risks include acute pancreatitis, cholelithiasis (gallbladder disease precipitated by rapid weight loss), and acute kidney injury secondary to severe dehydration.
Furthermore, all GLP-1 receptor agonists carry an FDA black-box warning regarding thyroid C-cell tumors based on pre-clinical rodent studies. Consequently, semaglutide is strictly contraindicated in patients with a personal or familial history of Medullary Thyroid Carcinoma (MTC) or Multiple Endocrine Neoplasia syndrome type 2 (MEN 2).
A Measured Clinical Perspective
Semaglutide represents an undeniable, monumental breakthrough in metabolic medicine. For individuals navigating chronic clinical obesity, intractable insulin resistance, and heightened cardiovascular risk profiles, it offers a therapeutic lever previously attainable only through bariatric surgery.
However, treating high-potency receptor agonists as casual, short-term vanity tools carries real physiological costs.
Sustainable health requires a clear-eyed perspective: semaglutide can powerfully reset metabolic setpoints, reduce systemic inflammation, and quiet chronic neurological hunger signals. Yet its successful, long-term implementation demands clinical supervision, structured resistance training to defend functional muscle, comprehensive nutritional education, and a realistic understanding that managing metabolic health is a lifelong continuum, not a temporary injection cycle.





